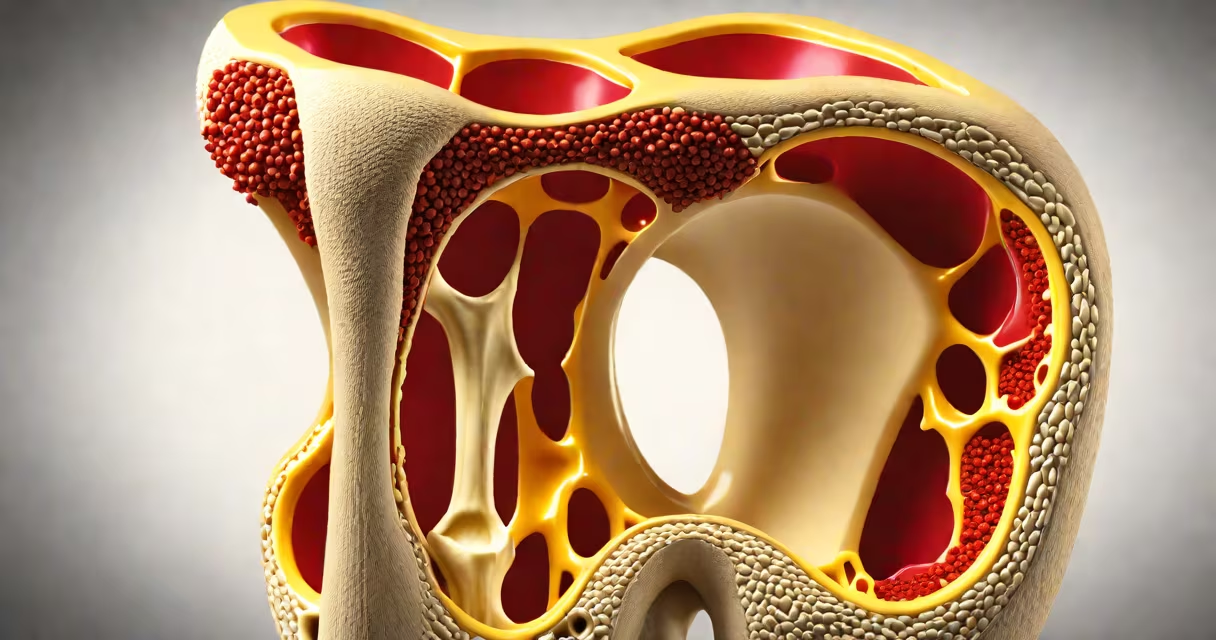
There are two main types of bone marrow: red marrow and yellow marrow. Red marrow produces blood cells, while yellow marrow stores fat and can convert back to red marrow under stress. These types differ in composition, location, and function throughout life.
Bone marrow is the soft, spongy tissue inside bones that generates all blood cells through hematopoiesis. This process begins in the yolk sac during early development, shifts to the liver and spleen in fetal stages, and finally settles in the bone marrow by birth.
Red marrow contains hematopoietic stem cells that differentiate into red blood cells, white blood cells, and platelets. These cells travel through the bloodstream to deliver oxygen, fight infection, and support clotting. Without functional red marrow, conditions like anemia or leukopenia develop rapidly.
Yellow marrow consists mostly of adipocytes (fat cells) and supports energy storage. While it doesn't produce blood cells under normal conditions, it can revert to red marrow during severe blood loss or chronic anemia, a process called marrow reserve activation. This conversion occurs in response to erythropoietin signaling from the kidneys.
The two types are defined by cellular makeup and function:
A 2021 study published in Cell Stem Cell confirmed that adult human red marrow maintains a stable niche for hematopoietic stem cells, with specific stromal cell subtypes providing structural and molecular support. Yellow marrow lacks this infrastructure and does not sustain blood cell production unless activated.
At birth, nearly all marrow is red. By age 25, about 50% of marrow in long bones converts to yellow. This shift reduces metabolic demand and increases fat storage capacity. The remaining red marrow is concentrated in the axial skeleton and proximal limb bones.
Clinically, marrow type affects diagnostic procedures. A bone marrow biopsy often targets the iliac crest because it contains abundant red marrow and is accessible. In contrast, yellow marrow samples yield little hematological data but may be used in fat tissue research.
When patients undergo chemotherapy or suffer from aplastic anemia, doctors assess marrow cellularity. A low red marrow count indicates poor blood cell production. In such cases, imaging like MRI can distinguish red from yellow marrow based on signal intensity-red marrow appears bright on T1-weighted images due to high iron content.
Many assume bone marrow is uniform. It is not. The term "marrow" refers to both types, but they serve different purposes. Confusing them leads to misinterpretation of medical scans or biopsies.
Another misconception is that yellow marrow is inactive. It is metabolically active and contributes to endocrine regulation. Adipocytes in yellow marrow secrete leptin and adiponectin, influencing insulin sensitivity and appetite control. A 2019 study in Nature Metabolism showed that marrow adipocytes increase in osteoporosis, suggesting a role in bone density regulation.
Also, people often think marrow only produces red blood cells. It generates all formed elements: granulocytes, monocytes, lymphocytes, megakaryocytes, and their derivatives. For example, a single hematopoietic stem cell can give rise to over 100 billion red blood cells per day in healthy adults.
| Feature | Red Marrow | Yellow Marrow |
|---|---|---|
| Primary Function | Hematopoiesis (blood cell formation) | Fat storage and potential red marrow conversion |
| Location in Adults | Pelvis, sternum, ribs, vertebrae, proximal femur and humerus | Diaphyses of long bones (femur, tibia, humerus) |
| Cellular Composition | Stem cells, myeloid/lymphoid precursors, erythroblasts | Adipocytes (>80%), few residual stem cells |
| Imaging Appearance (MRI) | High signal on T1-weighted images | Very high signal on T1-weighted images |
| Reversible Conversion | Cannot convert to yellow | Can convert to red under stress (e.g., hemorrhage) |
A 62-year-old woman presents with fatigue and low hemoglobin. A CBC shows anemia. A bone marrow biopsy from her iliac crest reveals hypocellular marrow with 20% cellularity and predominantly fatty tissue. MRI confirms extensive yellow marrow replacement in the femur.
These findings indicate aplastic anemia. The absence of red marrow activity explains the low blood counts. Treatment includes immunosuppressants and growth factors to stimulate residual red marrow. In rare cases, stem cell transplantation may be needed.
This case illustrates that marrow type matters in diagnosis. If the biopsy had been taken from the femoral shaft instead, it might have missed the underlying pathology due to dominant yellow marrow.
I observed a live bone marrow aspiration during a hematology rotation. The needle entered the posterior iliac crest. The syringe filled with a thick, reddish fluid-characteristic of active red marrow. The sample was sent for flow cytometry and histology. Within hours, we confirmed normal hematopoiesis. The contrast between that sample and a later one from a patient with leukemia-where abnormal blasts dominated-was stark. The color and consistency were immediate indicators of marrow health.
Red and yellow marrow are distinct biological tissues with specialized roles. Knowing how many types of bone marrow there are-two-is essential for accurate diagnosis, treatment planning, and understanding human physiology.