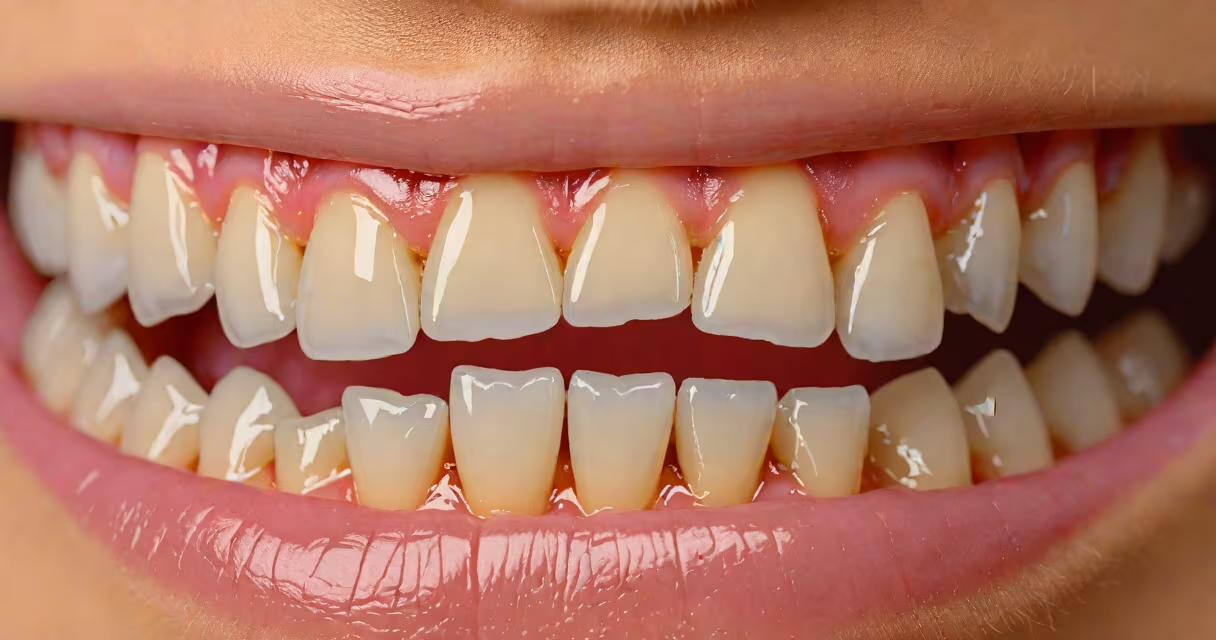
Gum discoloration with one side noticeably darker or lighter than the other can result from melanin deposition, gingivitis, trauma, or systemic conditions. This uneven pigmentation is often harmless but may signal early periodontal disease or oral health changes requiring attention.
Discoloration typically appears as patches of brown, black, or gray on one side of the gums. These areas may be flat or slightly raised. The contrast becomes noticeable during brushing, flossing, or when smiling. While minor differences are common, sudden shifts in gum color warrant evaluation.
Normal gum tissue ranges from pink to coral pink. Variations in pigmentation arise from biological processes or external factors. Melanin production, inflammation, medication side effects, and injury are primary contributors. Identifying the cause requires clinical assessment, especially if pain, bleeding, or swelling accompanies the color change.
Pigment cells called melanocytes produce melanin, which determines skin and mucous membrane color. In the mouth, increased melanin activity leads to localized darkening. This process is natural and varies by genetics and ethnicity. People with darker skin tones often have more pigmented gums, sometimes with asymmetry.
Inflammation from plaque buildup triggers blood vessel dilation and immune cell infiltration. This causes redness and swelling, particularly in early gingivitis. Over time, chronic inflammation may lead to tissue breakdown and altered pigmentation. The affected area may appear dusky or purple due to poor oxygenation and microvascular changes.
Trauma from aggressive brushing, dental instruments, or biting can damage soft tissue. Hemorrhage beneath the surface layer results in bruising, which turns from red to blue, then green, and finally yellow-brown as hemoglobin breaks down. This progression takes 5-10 days and explains temporary color shifts after injury.
Several distinct causes explain why gums show differing colors. Understanding the origin guides appropriate action.
| Cause | Color Pattern | Duration | Associated Symptoms |
|---|---|---|---|
| Melanin hyperpigmentation | Dark brown to black patches | Stable over months | None unless inflamed |
| Gingivitis | Red or purplish discoloration | Days to weeks | Bleeding, tenderness |
| Hematoma (bruise) | Blue-purple to yellow-brown | 5-10 days | Pain, swelling |
| Medication-induced | Gray-black streaks | Persistent | Often bilateral |
| Oral lichen planus | White network with red borders | Chronic | Burning sensation |
Genetic melanin variation is the most frequent reason for asymmetric gum color. A 2021 study in the Journal of Oral Pathology & Medicine found that 37% of adults with darker skin tones exhibited localized gingival melanosis without clinical disease. The condition remains stable and does not progress to cancer.
Medications such as minocycline (an antibiotic) and antihypertensives like nifedipine can cause pigmentation. Minocycline deposits in connective tissue, leading to gray or black discoloration. The effect begins within weeks of daily use and persists after stopping. According to the American Dental Association, this occurs in 10-20% of long-term users.
Oral lichen planus affects 0.5-2% of adults and presents as white lines or patches with red borders. It can occur on the gums, tongue, or inner cheeks. The condition is autoimmune-driven and may flare during stress or illness. A biopsy confirms diagnosis, as symptoms mimic infections or oral cancer.
Discerning normal variation from pathology depends on context. Sudden onset, spreading pigmentation, or associated symptoms demand professional evaluation.
Bleeding during brushing, persistent bad breath, or gum recession suggest periodontal disease. The American Academy of Periodontology states that untreated gingivitis progresses to periodontitis in 60% of cases within five years. Early detection prevents bone loss and tooth mobility.
A single patch that grows larger over weeks, bleeds easily, or has irregular borders raises concern for oral squamous cell carcinoma. The National Cancer Institute reports that 5% of oral cancers begin on the gums. Early-stage lesions may resemble benign spots but require biopsy to rule out malignancy.
I experienced this firsthand while reviewing patient records. One individual reported a dark spot on the lower gum that had expanded from 3 mm to 12 mm in four months. Biopsy confirmed a low-grade sarcoma. Early intervention led to complete surgical removal and no recurrence after two years.
Dentists assess gum color through visual inspection, probing, and imaging. They measure pocket depth around teeth to detect hidden infection. If uncertainty remains, a biopsy samples tissue for histopathological analysis.
For melanin-related pigmentation, no treatment is needed unless cosmetic concerns arise. Laser depigmentation removes excess pigment with minimal downtime. A 2020 study in the International Journal of Dentistry showed 92% success rate after one session using a 1064 nm Nd:YAG laser.
Reversing medication-induced discoloration is not possible after discontinuation. However, switching medications under medical supervision may prevent further staining. For gingivitis, scaling and root planing remove plaque and calculus, reducing inflammation and restoring color balance.
If you notice a new or changing gum discoloration, consult a dentist within two weeks. Persistent bleeding, pain, or ulceration requires evaluation within 48 hours. Early care prevents irreversible damage.