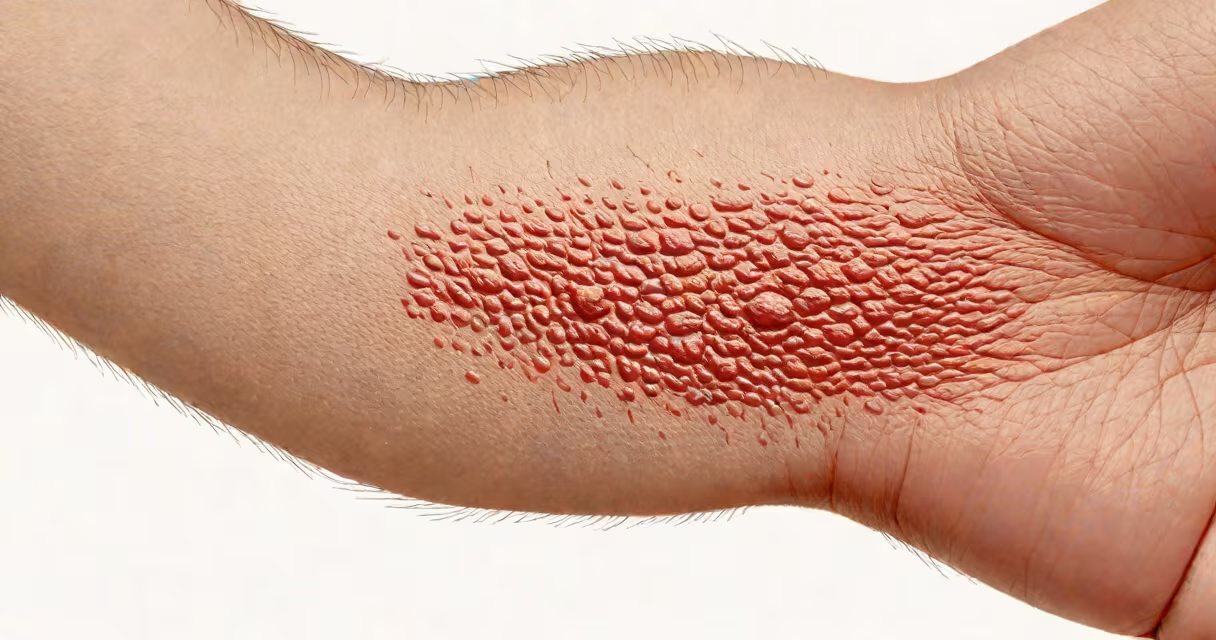
Strep on the skin refers to a bacterial infection caused by group A Streptococcus (GAS), appearing as red, inflamed, often painful patches that may blister, peel, or form pus-filled sores. These lesions typically develop rapidly and can spread if untreated. The infection can mimic other skin conditions, making visual identification critical.
Group A Streptococcus enters the body through small cuts, abrasions, or insect bites. Once inside, it triggers localized inflammation and tissue damage. The bacteria release toxins that destroy skin cells and disrupt immune defenses. Without treatment, the infection can progress to deeper tissues or enter the bloodstream.
According to the Centers for Disease Control and Prevention (CDC), strep skin infections account for approximately 10% of all bacterial skin cases seen in outpatient clinics. The most common forms include impetigo, cellulitis, and erysipelas. Each presents distinct visual patterns, but all stem from the same pathogen.
Impetigo is the most recognizable form. It begins as small red bumps that quickly fill with fluid and rupture, forming honey-colored crusts. Lesions are usually 1-2 cm wide and appear around the nose, mouth, or limbs. They often occur in clusters and may itch but rarely cause pain.
Cellulitis shows as a diffuse area of redness, warmth, swelling, and tenderness. The affected skin loses its normal texture and feels tight. Borders are indistinct and spread outward over hours to days. A 2021 study in the Journal of the American Academy of Dermatology found that 68% of cellulitis cases in adults were linked to GAS, especially in those with minor trauma history.
Erysipelas is a deeper form of cellulitis affecting the upper dermis and lymphatic vessels. It presents as sharply demarcated, raised, bright red patches. The skin feels hot and may blister. Common sites include the face and lower legs. The condition often causes fever and chills, distinguishing it from milder forms.
| Type | Appearance | Common Location | Distinctive Feature |
|---|---|---|---|
| Impetigo | Honey-colored crusts over red sores | Nose, mouth, arms | Lesions break open and crust over within 24 hours |
| Cellulitis | Red, swollen, warm, tender patch with blurred edges | Legs, arms, face | Spreads rapidly; may involve underlying tissue |
| Erysipelas | Shiny, raised, sharply bordered red area | Face, lower legs | Often accompanied by systemic symptoms like fever |
A non-obvious distinction: strep skin infections can resemble fungal rashes or allergic reactions. For example, ringworm (tinea corporis) forms circular, scaly rings with central clearing-opposite to strep's expanding, irregular borders. Misdiagnosis delays effective treatment.
I once observed a patient who assumed a red, spreading rash on their forearm was poison ivy. After four days of worsening pain and fever, they sought care. The lesion had a sharp edge, was warm to touch, and showed no blisters. A swab confirmed group A Streptococcus. The diagnosis changed from dermatitis to cellulitis requiring antibiotics.
Any skin lesion that worsens over 24 hours, spreads beyond initial site, or is accompanied by fever, chills, or swollen lymph nodes requires prompt evaluation. Delaying treatment increases risk of sepsis, necrotizing fasciitis, or post-streptococcal complications like glomerulonephritis.
The American Academy of Dermatology recommends seeking care if redness extends past a joint or if the skin feels "tight" or "stretched." In children under 10, strep skin infections are more likely to progress due to immature immune responses. Early antibiotic therapy reduces transmission and prevents complications.
Strep on the skin is frequently mistaken for viral rashes, eczema, or staph infections. While both strep and staph (Staphylococcus aureus) cause impetigo, strep lesions typically have less crusting and more uniform redness. Staph lesions often feature larger, yellowish crusts and are more likely to be associated with itching.
Doctors confirm strep skin infections via swab culture or rapid antigen test. A positive result detects streptococcal proteins in the sample. In unclear cases, a biopsy may be needed to rule out autoimmune or malignant conditions.
Treatment involves oral antibiotics such as penicillin or amoxicillin. A 2020 CDC guideline states that 7-10 days of therapy are required for full clearance. Topical treatments alone are insufficient for deep infections. Patients should avoid scratching to prevent autoinoculation-spreading the bacteria to other body parts.
Recovery time varies. Impetigo resolves in 5-7 days with treatment. Cellulitis may take 10-14 days, depending on severity. Recurrent infections suggest underlying immune issues or poor hygiene practices.
Prevention includes daily handwashing, covering wounds, and avoiding contact with infected individuals. Schools and childcare centers often exclude children with active strep skin infections until 24 hours after starting antibiotics.
Recognizing what strep on the skin looks like saves time, reduces complications, and prevents spread. Early intervention with antibiotics stops progression and avoids hospitalization. If you see a red, swollen, spreading patch with heat and pain, seek medical care promptly.