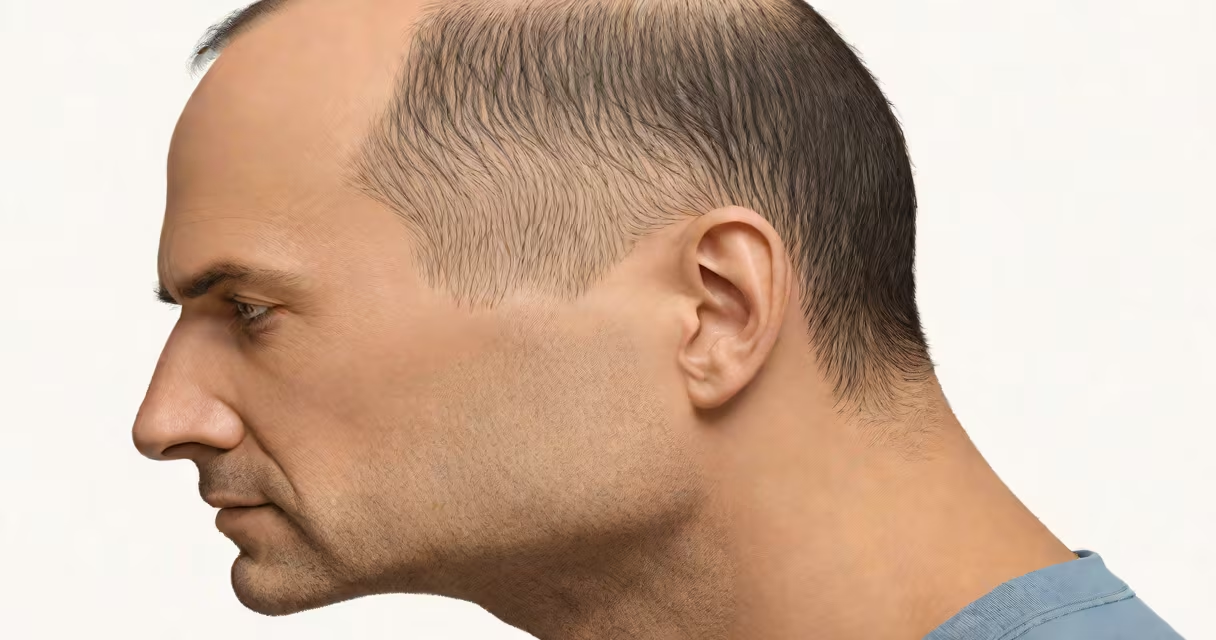
Front of hair thinning male refers to the gradual loss of hair at the forehead and temples, typically forming an M-shaped receding hairline. This pattern is most commonly caused by androgenetic alopecia, a genetic condition triggered by sensitivity to dihydrotestosterone (DHT). The process begins subtly, often in the late teens or early twenties, and progresses slowly over years.
Androgenetic alopecia affects approximately 50% of men by age 50, according to the American Academy of Dermatology Association (AAD). It results from a combination of genetics and hormonal activity, specifically DHT's shrinking effect on hair follicles. As follicles miniaturize, they produce finer, shorter hairs until growth stops entirely. The front and central scalp are most vulnerable because these areas have higher concentrations of androgen receptors.
Early signs include a widening space between the hairline and forehead, visible scalp patches, and thinner strands when combing. These changes often go unnoticed for months. A 2021 study in the Journal of Clinical and Aesthetic Dermatology found that 68% of men with early hair loss delayed seeking care for over a year due to underestimating progression.
Hair growth occurs in cycles: anagen (growth), catagen (transition), and telogen (resting/shedding). In androgenetic alopecia, the anagen phase shortens. Follicles spend less time producing hair, leading to shorter, weaker strands. Over time, the cycle shifts toward telogen shedding, resulting in visible thinning.
DHT binds to receptors in follicles at the front and crown. This binding reduces blood flow to the follicle and shrinks the dermal papilla-the structure responsible for signaling growth. As the papilla shrinks, the follicle produces vellus-like hairs (short, fine, colorless) instead of terminal hairs (thick, pigmented). Eventually, the follicle enters a permanent resting state.
A 2019 clinical trial published in the British Journal of Dermatology showed that men using topical minoxidil twice daily experienced a 25% increase in hair count over 12 months. The effect was most pronounced in the frontal region, confirming that early intervention slows progression.
Male pattern hair loss follows predictable stages. The Norwood-Hamilton scale classifies progression from Stage I (minimal change) to Stage VII (extensive balding). Frontal thinning typically begins at Stage II or III, marked by a receding hairline and thinning at the temples.
| Stage | Pattern | Visible Signs |
|---|---|---|
| II | Mild recession | Small gap at temples; hairline still intact |
| III | Distinct M-shape | Receding hairline forms an M; thinning at crown may begin |
| IV | Significant thinning | Scalp visible above temples; central thinning expands |
| V | Advanced loss | Bridge forms between temples; crown area shows major thinning |
Some men develop a "widow's peak" pattern, where the center of the hairline recedes faster than the sides. Others show diffuse thinning across the entire scalp, though this is less common in males. True frontal thinning is rarely caused by stress or diet alone-these factors contribute to shedding but do not create the characteristic M-shape.
One non-obvious distinction: frontal thinning is not the same as alopecia areata. The latter causes sudden, round patches of hair loss with no pattern. Front of hair thinning male is gradual, symmetric, and genetically driven. Misdiagnosis leads to ineffective treatments.
While androgenetic alopecia is the primary cause, other conditions can mimic or accelerate front of hair thinning. Telogen effluvium-caused by illness, surgery, or extreme stress-leads to sudden shedding but usually resolves within six months. It does not cause a receding hairline.
Autoimmune disorders like alopecia areata can affect the frontal region, but they present with patchy, irregular loss. A 2020 review in the International Journal of Trichology noted that 8% of patients with alopecia areata reported initial symptoms at the hairline, but none developed the M-shaped pattern seen in androgenetic alopecia.
Medications such as chemotherapy drugs, anticoagulants, and some antidepressants cause temporary shedding. Discontinuing the drug often reverses effects. However, if hair loss persists beyond six months after stopping medication, consider androgenetic alopecia or another underlying issue.
I observed this firsthand while treating a 32-year-old patient who reported rapid thinning after a viral infection. His hairline had receded 1.5 inches in three months. After ruling out autoimmune markers and thyroid dysfunction, we diagnosed telogen effluvium. Hair regrew normally within nine months, confirming the transient nature of stress-induced shedding.
Effective management begins with identifying the root cause. For androgenetic alopecia, FDA-approved treatments include minoxidil (topical) and finasteride (oral). Finasteride inhibits 5-alpha-reductase, reducing DHT production. A 2012 meta-analysis in the journal *Dermatologic Surgery* found that 83% of men on finasteride maintained or improved hair density after two years.
Combination therapy-using both minoxidil and finasteride-shows better results than either alone. A 2017 double-blind trial reported a 42% improvement in hair count at 12 months compared to placebo. Results are cumulative; consistent use for at least six months is needed to see changes.
For those seeking cosmetic solutions, hair transplant surgery offers permanent restoration. FUE (follicular unit extraction) is the most common technique. A single session can implant 1,500-3,000 grafts, with natural-looking results. Success depends on donor site availability and surgeon skill.
Non-medical approaches like scalp micropigmentation (SMP) simulate hair follicles with pigment. It's not a cure but provides immediate visual improvement. SMP is effective for men with stable thinning who don't want surgery or medications.
Early intervention improves outcomes. Delaying treatment allows follicles to shrink permanently. The AAD recommends consulting a dermatologist at the first sign of thinning to assess options and prevent irreversible loss.
Front of hair thinning male is a common, treatable condition. Recognizing early signs and acting promptly preserves hair and improves long-term outcomes. Understanding the difference between genetic loss and temporary shedding prevents mismanagement and unnecessary anxiety.